
Laparoscopic Appendectomy
Laparoscopic Appendectomy
David Ray Velez, MD
Table of Contents
Trocar Placement
Standard Placement
- 5-mm Port: Periumbilical
- 5-mm Port: Suprapubic
- 12-mm Port: Left Lower Quadrant
- Variations:
- *Some Prefer a Periumbilical Port with Two Left Sided Ports Instead to Avoid Bladder Injury without a Suprapubic
- *Some Place the 12-mm Port Periumbilical Instead
Placement In Pregnancy
- *Need to Avoid Gravid Uterus in Second and Third Trimesters
- First Trimester
- Normal Placement
- Second Trimester
- Access: Hasson (May Consider Veress at Subxiphoid or Left Costal Margin)
- Ports: Supraumbilical, Left Lower Quadrant, and Right Lower Quadrant
- Avoids Suprapubic Port
- Third Trimester
- Access: Hasson (Consider Veress Subxiphoid or Left Costal Margin)
- Ports: Supraumbilical and Two Along the Right Side
- Potential Options:
- Right Lower Quadrant
- Right Mid-Abdomen
- Right Upper Quadrant
- Subxiphoid
- Avoids Suprapubic and Left Lower Quadrant Ports
- Also Consider Positioning in Full or Partial Left Lateral Decubitus During the Second/Third Trimesters
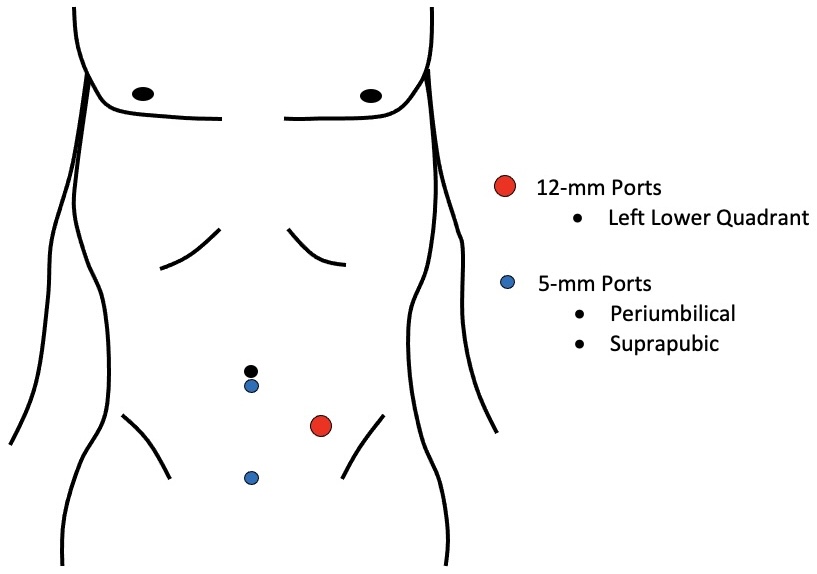
Trocar Placement
Procedure
Access the Abdomen
- Initial Position: Supine with Left-Arm Tucked
- Prep and Drape in the Standard Sterile Fashion
- Achieve Pneumoperitoneum by Preferred Method
- Veress Needle
- Hasson
- OptiView Optical Trocar
- Place Trocars in Appropriate Position (See Above)
- Complete Patient Positioning with Head Down (Trendelenburg) with Left-Side Down (Left Lateral Decubitus)
Dissection
- Identify and Expose the Appendix Along its Length from Base to Tip
- Bluntly Create a Tunnel Through the Mesoappendix at the Base
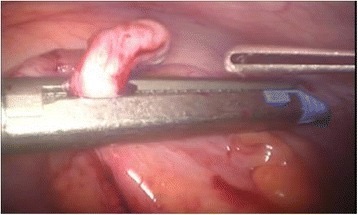
- Staple Across the Base of the Appendix
- Generally Use a Blue Staple Load (3.5 mm)
- Staple Across the Mesoappendix Near the Appendix
- A Small Retrospective Study Reported Significantly Less Postoperative Bleeding with a Grey Staple Load (2.0 mm) Compared to a White Staple Load (2.5 mm); However This Finding Has Not Been Definitively Established
- Variations:
- Can Staple the Mesoappendix First and the Appendiceal Base Second
- May Use an Energy Device to Divide the Mesoappendix (LigaSure, Harmonic, EnSeal, etc)
- No Significant Difference in Postoperative Bleeding Has Been Demonstrated Between Stapler or Energy Device Division of the Mesoappendix
Completion
- Remove Appendix Through the 12-mm Trocar Site Using an Endoscopic Bag
- Aspirate Overt Fluid but Avoid Peritoneal Irrigation
- Routine Irrigation Has Not Been Shown to Reduce Intra-Abdominal Abscess or Surgical-Site Infection Compared with Suction Alone
- Irrigation May Theoretically Disseminate Contamination and Increases Operative Time – Therefore, Suction Alone is Generally Preferred for Complicated Appendicitis
- Ensure Hemostasis
- Close the Fascia of the 12-mm Port Site to Reduce the Risk of Port-Site Hernia
- Carter-Thomason/PMI Device
- Suture Passer
- Direct Closure
- Release Pneumoperitoneum
- Close Skin
Laparoscopic Appendectomy 1
Complications
Overall Complication Rate: 10-30%
Surgical Site Infection
- The Most Common Complication After Appendectomy
- Laparoscopic Risk:
- Wound Infection: 1.9-3.7%
- Intraabdominal Abscess: 2-4% Overall (6-10% if Perforated)
- Comparison to Open Approach:
- Laparoscopic Approach Has a Significantly Decreased Risk for Wound Infection (OR 0.30-0.52)
- Laparoscopic Approach Actually Has a Significantly Increased Risk for Intraabdominal Abscess (OR 1.56-2.29)
- Management:
- Antibiotics for Cellulitis, Abscess, or Any Systemic Infection
- Open/Drain Localized Superficial Infection if Appropriate
- Consider Percutaneous Drainage for Any Intraabdominal Abscess
Hemorrhage
- Sources:
- Mesoappendix/Staple Line
- Appendiceal Artery Injury
- Abdominal Wall/Epigastric Vessel Injury
- Overall Risk: 1%
- Management:
- Intraoperative Identification: Achieve Hemostasis with Clips, Sutures, Staplers or Energy Device as Needed
- Consider Conversion to Open for Uncontrolled Hemorrhage
- Postoperative Identification: Blood Transfusion as Indicated and Consideration of Angioembolization vs Repeat Surgery
- Intraoperative Identification: Achieve Hemostasis with Clips, Sutures, Staplers or Energy Device as Needed
Stump Appendicitis
- Definition: Recurrent Appendicitis Due to Incomplete Appendectomy Leaving an Excessively Long Stump
- Clinical Presentation Generally Mimics that of Classic Appendicitis
- Preventative Measures:
- Clearly identify the Cecum
- Complete Appendix Resection
- Securely Close the Stump with an Endoloop or Stapler
- Minimal Stump Length (Ideally < 5 mm)
- Inspect for Anatomical Variations
- Ensure Hemostasis and Absence of Residual Tissue
- Management: Completion Appendectomy/Stump Resection
- May Require Partial Cecectomy for Complete Resection
- May Require Ileocecectomy vs Right Hemicolectomy if Severe
Other Complications
- Bowel Injury – From Trocar Placement, Dissection, or Energy Devices
- Bladder Injury – From Suprapubic Trocar Placement
- Postoperative Urinary Retention (POUR)
- Venous Thromboembolism (VTE)
- Ileus
- Port-Site Hernia
- Adhesive Small Bowel Obstruction
References
- Strzałka M, Matyja M, Rembiasz K. Comparison of the results of laparoscopic appendectomies with application of different techniques for closure of the appendicular stump. World J Emerg Surg. 2016 Jan 6;11:4. (License: CC BY-4.0)